Staurosporine (STS) Evaluation and CINSARC Genomic Profiling in Soft Tissue Sarcoma
Copy code to add this image to your page
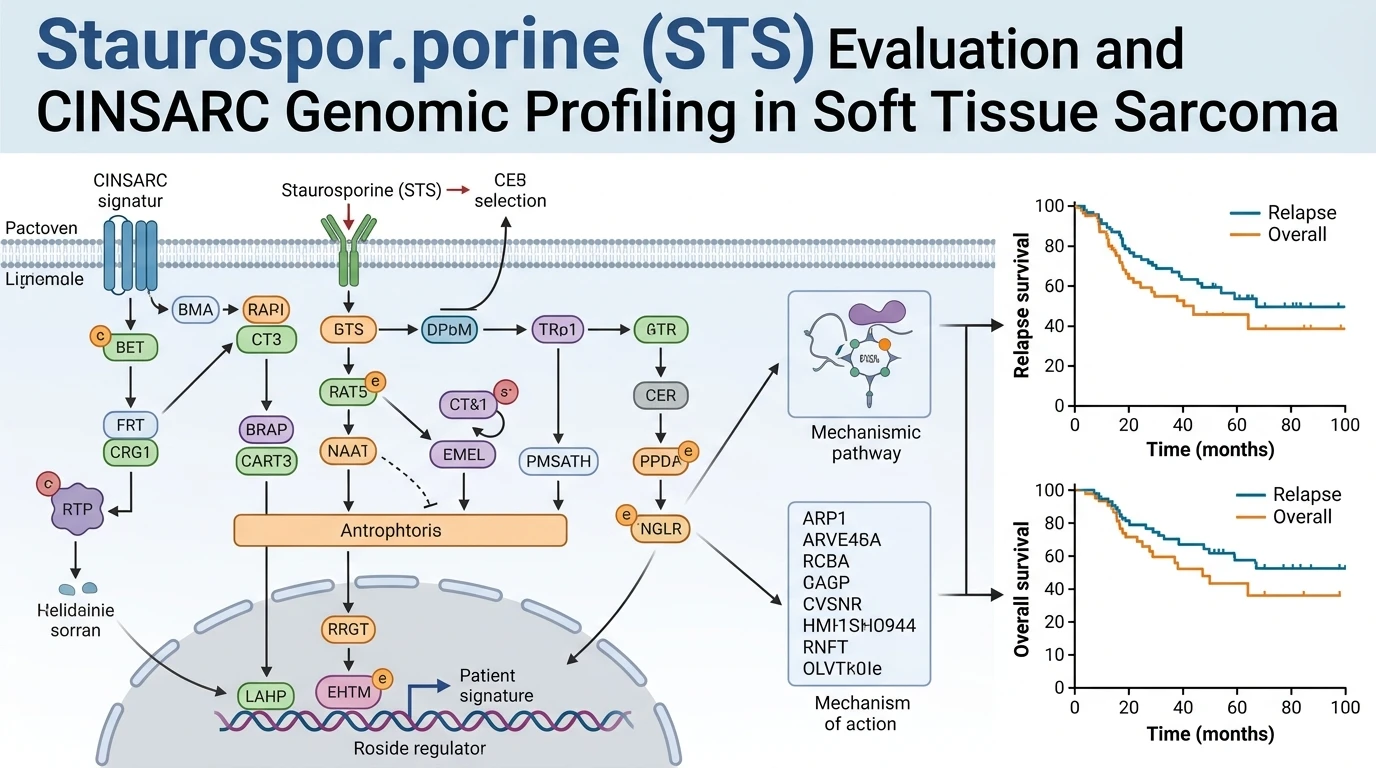
Soft tissue sarcomas represent a heterogeneous group of mesenchymal malignancies characterized by distinct genomic profiles, varying from karyotypically simple translocation-driven subtypes to complex karyotypes defined by profound chromosomal instability. Within complex-karyotype sarcomas, transcriptomic signatures targeting mitotic fidelity and chromosomal architecture have been advanced to refine clinical risk assessment beyond traditional clinicopathological nomograms. Among these molecular tools, the CINSARC 67-gene expression signature (genes involved in mitosis control and chromosome integrity) was established to quantify genomic complexity by measuring transcript abundance across key mitotic regulators, including polo-like kinases, aurora kinases, kinesin motor proteins, and cyclin-dependent kinase complexes. In experimental oncology and pharmacological profiling, pan-kinase inhibitors such as Staurosporine (STS) are routinely employed as reference compounds to perturb ATP-binding pockets within these mitotic signaling nodes, referencing defined kinase catalytic domain structures to interrogate pathway dependence, spindle assembly checkpoint signaling, and induced apoptotic cascades.
The mechanistic premise of CINSARC rests on the hyperactivation of mitotic machinery. Overexpression of genes involved in chromosome condensation, kinetochore assembly, and sister chromatid cohesion correlates with high tumor grade and elevated risk of metastatic dissemination in retrospective, non-homogeneously treated cohorts. However, the prognostic robustness of transcriptomic signatures must be validated within prospective, controlled clinical trials where standardized systemic therapy is administered.
To establish whether transcriptomic prognostic stratification and genomic complexity profiling in Soft Tissue Sarcoma (STS) holds clinical utility under contemporary therapeutic protocols, investigator-led studies systematically evaluated CINSARC within the prospective phase III ISG-STS 1001 trial cohort. This clinical trial evaluated full-dose neoadjuvant chemotherapy—specifically histotype-tailored chemotherapy versus standard full-dose anthracycline plus ifosfamide—in 86 patients with localized, high-risk soft tissue sarcoma of the extremities or trunk wall. Tumor tissue samples harvested prior to neoadjuvant therapy underwent gene expression profiling, resulting in patient stratification into two primary transcriptomic risk categories: CINSARC low-risk (C1, n=30) and CINSARC high-risk (C2, n=56).
Standard clinical risk stratification in localized soft tissue sarcoma relies on validated clinicopathological models, prominently the SARCULATOR nomogram, which integrates patient age, tumor diameter, histological subtype, and French Federation of Cancer Centers Sarcoma Group (FNCLCC) grade. Comparative evaluation between CINSARC class assignment and SARCULATOR-predicted risk demonstrated a Cohen's kappa coefficient of 0.174. This low concordance coefficient underscores a profound divergence between transcriptomic metrics of chromosome integrity and clinical risk models. High-risk histological features do not uniformly align with elevated CINSARC transcriptomic scores in localized disease.
Longitudinal clinical outcome evaluations across the 86 trial participants demonstrated no statistically significant differences in disease control between the C1 and C2 transcriptomic risk groups under uniform neoadjuvant therapy. The 5-year relapse-free survival (RFS) rate reached 0.57 in the C1 low-risk cohort versus 0.55 in the C2 high-risk cohort (p=0.481). Analysis of 5-year metastasis-free survival (MFS) demonstrated nearly identical outcomes between groups, yielding 0.63 for C1 and 0.64 for C2 (p=0.740). Furthermore, 5-year overall survival (OS) showed no statistically significant separation, recording 0.80 for C1 low-risk patients compared to 0.72 for C2 high-risk patients (p=0.460).
These empirical findings demonstrate that the baseline prognostic power of CINSARC is limited in localized high-risk soft tissue sarcoma managed with prospective neoadjuvant chemotherapy regimens. While mitotic gene overexpression correlates with aggressive biological behavior in untreated context, intensive cytotoxic chemotherapy appears to mitigate the adverse prognostic impact associated with high transcriptomic complexity.
Transcriptomic Stratification and Therapeutic Response Analysis
Copy code to add this image to your page
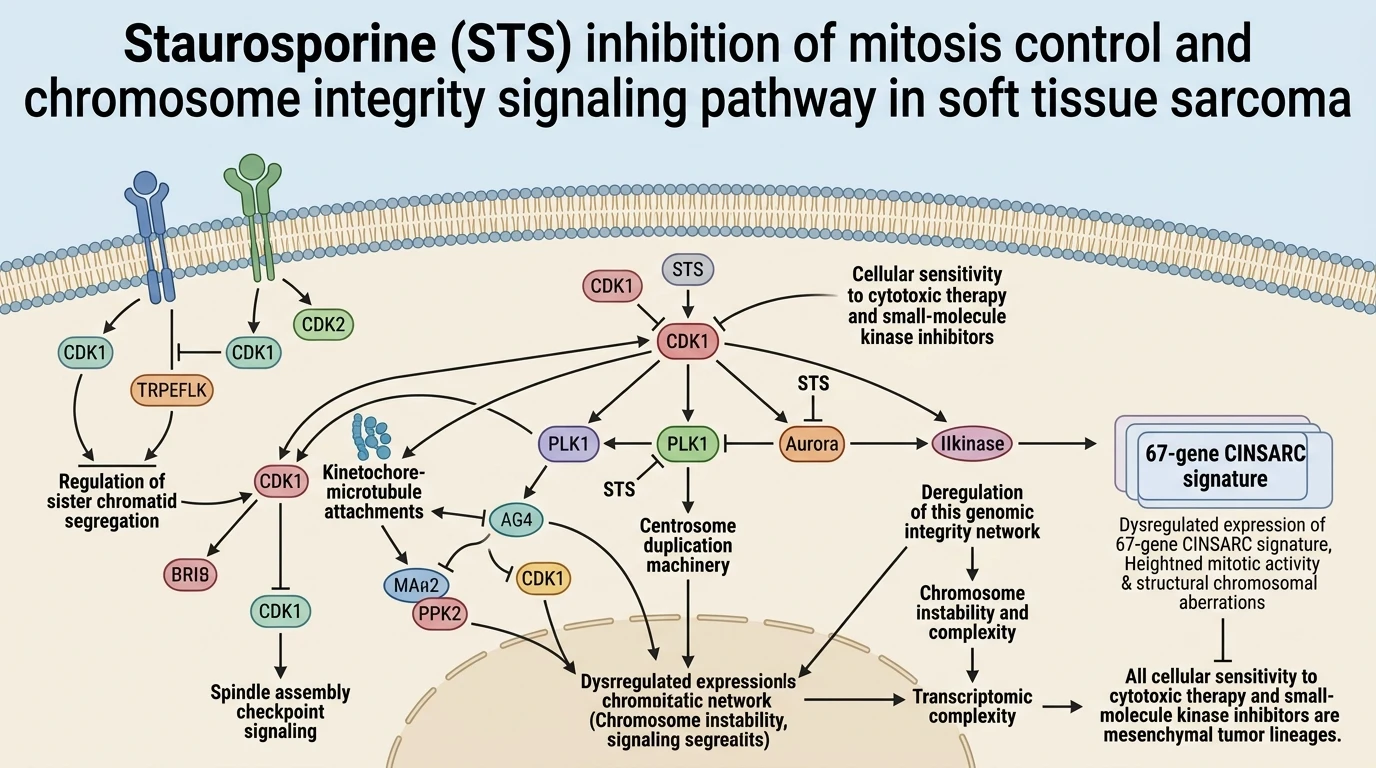
The CINSARC 67-gene signature measures transcriptomic expression of mitotic control and chromosome integrity genes in soft tissue sarcoma. Evaluated within the prospective phase III ISG-STS 1001 trial cohort of 86 high-risk localized sarcoma patients receiving neoadjuvant chemotherapy, CINSARC showed low concordance with the SARCULATOR nomogram (kappa = 0.174). No significant differences were observed between low-risk (C1) and high-risk (C2) groups for 5-year relapse-free survival (0.57 vs 0.55), metastasis-free survival (0.63 vs 0.64), or overall survival (0.80 vs 0.72). Findings indicate limited prognostic value for CINSARC in localized STS treated with neoadjuvant chemotherapy.
Discordance Between Transcriptomic Risk and Nomogram-Based Stratification
The correlation between clinicopathological nomograms and molecular risk classifiers remains a critical focus in sarcoma biology. In the ISG-STS 1001 trial cohort, the agreement between SARCULATOR predictions and CINSARC classification was low. Cohen's kappa reached only 0.174. This low value indicates that histological grading and tumor size capture distinct biological features from transcriptomic mitotic complexity. In experimental models, broad kinase inhibition by Staurosporine (STS) disrupts these mitotic checkpoints across both C1 and C2 transcriptomic phenotypes. Cellular response to kinase perturbation does not strictly correlate with baseline transcript abundance. Consequently, clinical risk models relying solely on transcriptomic signatures may misclassify risk in patients undergoing aggressive systemic treatment.
Neoadjuvant Chemotherapy Attenuates CINSARC Prognostic Separation in High-Risk Sarcoma
Systemic therapy significantly alters the expected natural history of localized high-risk soft tissue sarcoma. In untreated historical cohorts, high CINSARC expression correlated with rapid disease recurrence and early metastatic spread. However, prospective evaluation demonstrated equalized 5-year metastasis-free survival rates of 0.63 in C1 and 0.64 in C2. Neoadjuvant anthracycline and ifosfamide combination therapy appears to eradicate micro-metastatic disease irrespective of baseline CINSARC status. Relapse-free survival curves showed no statistically significant divergence over five years. These observations indicate that high-risk transcriptomic features do not confer inherent resistance to intensive chemotherapy. Baseline mitotic signature expression alone cannot guide neoadjuvant treatment decisions in localized disease.